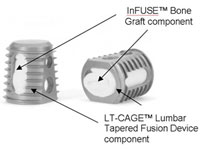
A Yale University project examining patient-level data from Medtronic‘s (NYSE:MDT) Infuse bone morphogenetic protein revealed results from a pair of independent research teams showing that the recombinant human bone morphogenetic protein-2 used in Infuse is equivalent to the gold standard for spinal fusion procedures, iliac crest bone grafts.
Medtronic paid $2.5 million to Yale and provided all of the data in its possession on Infuse for the studies, carried out by teams at England’s York University and the Oregon Health & Science University, after a controversial June 2011 issue of the Spine Journal claimed that the risk of adverse events with Infuse could be as high as 50%.
But the Oregon group’s review found that Medtronic-sponsored early trials of the Infuse rhBMP-2 product were biased.
"Articles by Medtronic-associated investigators underreported adverse events in the rhBMP-2 and ICBG groups. As noted previously, these articles reported ‘no adverse events due to rhBMP-2’ and ‘no unanticipated device-related adverse events.’ In the control group, the articles emphasized ‘donor site hip pain,’ which was assessed only in the control patients and only on the side of the iliac crest operation," the Oregon reviewers wrote.
The York group did not asses the reliability of early Infuse research articles.
"This shows us yet again that conclusions not based on a careful synthesis of all available evidence can be misleading. For that reason, Annals considers systematic reviews to be the best evidence for clinical practice," the journal’s editors wrote.
Chris O’Connell, president of Medtronic’s restorative therapies group, stressed to MassDevice.com that the pre-market approval studies of Infuse were designed to prove equivalence with ICBG, saying that the 2 Yale reviews confirmed early findings.
"At the end of the day, we got reports that were consistent with what we’ve seen over time, which is a lot of great benefits from this product and continuing questions about the product that we will continue to invest in studying, and a product that we believe is safe and effective," O’Connell told us. "This product is a very unique product in orthopedic medicine. It remains, in our view, a very important treatment option. We’re extremely proud of the act we took to expose the entirety of the data to independent review. I think it had the intended outcomes, in terms of reinforcing the positives but also confirming the ongoing questions.
"We’re committed to answering those questions through ongoing research," O’Connell told us. "At the end of the day, we want to be a part of what is a broader theme in the medical device industry, which is open access to data and confirming increasing standards of clinical evidence."
News of the Yale studies, published today in the Annals of Internal Medicine, prompted a flurry of responses from the spinal surgery world, including an editorial by Dr. Eugene Carragee, editor-in-chief of the Spine Journal and a response from Robin Young, publisher and editor of Orthopedics This Week.
"In some cases, an extraordinary merry-go-round of comprehensively conflicted faces are found at each check and balance: In one instance, it seems the principal investigator with strong financial ties to Medtronic helped design a trial, and then the same person acted as the surgeon and, for consistency, monitored complications, then went on to author the paper, whose drafts were written in whole or in part with the company, and then submitted the manuscript for review to…well…himself as editor in chief or section editor of the journal!" Carragee wrote. "In some cases the editor in chief of the journal reviewing his own paper was also, in fact, both the developer and the royalty holder on one or more products being investigated. It would be hard to envision a situation less likely to produce an unbiased journal publication. And now the [Yale Open Data Access Project] group – echoing The Spine Journal’s critical review from 2 years ago – tells us that important concerns about BMP-2 complications were ‘underreported’ or just missing. As YODA project director Harlan Krumholz, MD, SM, delicately puts it, ‘Evidence suggests that some data are not missing at random.’ Annals editors are more blunt: ‘Early journal publications misrepresented the effectiveness and harms through selective reporting, duplicate publication, and underreporting.’ Ouch."
In his riposte, Young accused Carragee of making his own misrepresentations, citing the York reviewers’ inability to confirm Carragee’s assertion that the risk of adverse events with Infuse ranges between 10 to 50 times IBCG.
"10x to 50x higher. So the authors checked that claim. Here is their conclusion: ‘Our review differs from the existing review (the authors then cited the Carragee study) in that we had access to more extensive and detailed data than did Carragee and colleagues’ and that after reviewing all of the data, the difference between the adverse events reported in the trial publications and actual adverse events was minimal," Young wrote. "Quoting from page 883, the results of their analysis for adverse events was inconclusive and ‘The only clear evidence of a difference was for pain at or shortly after surgery, which was more common in the rhBMP-2 recipients (odds ratio, 1.78),’" he wrote. "Not exactly 10x-50x. Not even 2x. That’s a mis-measurement of a scale that approaches scientific malpractice."
In the end, the upshot for spine doctors, according to both O’Connell and Drs. Daniel Resnick and Kevin Bozic (who also wrote an editorial for the Annals of Internal Medicine), is that "physicians ultimately have to decide the benefits and the risks," as the Medtronic executive put it to MassDevice.com.
"These findings are important for guiding clinical decision making. On the basis of them, using either autograft or rhBMP-2 to enhance fusion rates in patients having anterior lumbar interbody fusion or posterolateral fusion seems clinically reasonable, Resnick and Bozic wrote. "Patients should be counseled on the relative benefits and harms of each option and should be allowed to actively participate in decision-making. In some procedures, such as anterior lumbar interbody fusion, graft harvest is a separate procedure and avoiding a second incision and associated graft site pain may be well worth the exceedingly small increased risk for cancer. In posterolateral fusion procedures, locally harvested graft and ICBG are often available through the same incision. In these cases, it may not make sense to assume any increased risk, no matter how small. Given the higher complication rates noted in anterior cervical surgery, rhBMP-2 should not be used in this setting without a compelling reason – for example, during a pseudarthrosis repair or other salvage procedure. For posterior interbody procedures, such as posterior lumbar interbody fusion or transforaminal lumbar interbody fusion, the use of rhBMP-2 is associated with ectopic bone formation, and strategies to minimize the clinical effect of excessive bone growth should be used."
